


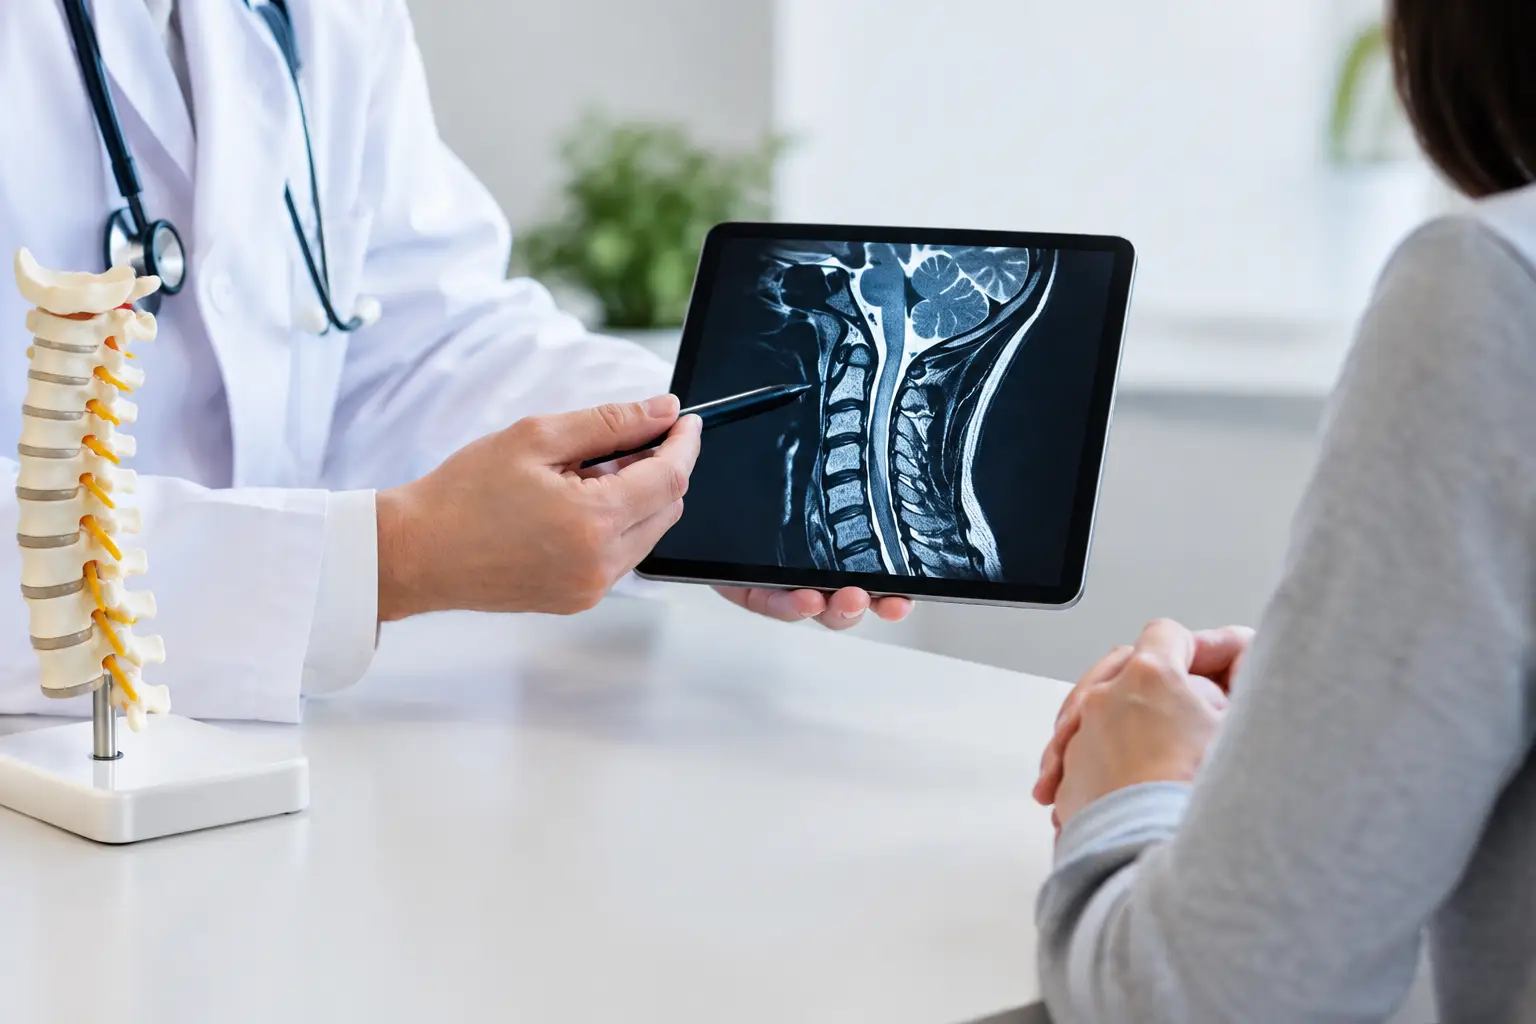
A hand that suddenly feels clumsy, an unsteady walk, or a growing sense of stiffness in both legs can be more than ordinary neck pain. Patients often ask, can cervical myelopathy cause paralysis? The direct answer is yes: severe or untreated compression of the spinal cord in the neck can lead to profound weakness and, in some cases, paralysis. It is not the outcome for every patient, but it is a risk that deserves timely, specialized evaluation.
Cervical myelopathy is a condition involving spinal cord dysfunction in the cervical spine, or neck. Because the spinal cord carries signals between the brain and the rest of the body, pressure in this area can affect balance, hand coordination, strength, sensation, and bladder or bowel function. The central concern is not simply neck pain. It is whether the spinal cord is being injured.
Can Cervical Myelopathy Cause Paralysis?
Cervical myelopathy can cause paralysis when spinal cord compression becomes severe enough to disrupt the nerve pathways controlling movement and sensation. More commonly, symptoms develop gradually, beginning with subtle hand weakness, trouble with buttons or handwriting, gait imbalance, leg stiffness, or numbness and tingling. Without appropriate treatment, damage may progress.
Paralysis is not inevitable. The course depends on the source and degree of compression, the length of time the cord has been affected, whether symptoms are worsening, and whether an injury occurs on top of existing spinal narrowing. A person with significant cervical stenosis may have limited symptoms for years, while another may decline more quickly.
A fall, car accident, or forceful neck extension can be particularly dangerous when the spinal canal is already narrow. In some cases, a relatively minor injury can trigger sudden spinal cord dysfunction. New weakness after trauma requires immediate medical attention.
What Causes the Spinal Cord to Become Compressed?
Age-related degeneration is a common cause of cervical myelopathy. Over time, discs can lose height, joints can enlarge with arthritis, and bone spurs can narrow the space around the spinal cord. A herniated disc, thickened spinal ligaments, spinal misalignment, or a cyst or tumor can also contribute to compression.
The diagnosis requires more than identifying arthritis on an imaging study. Many adults have degenerative changes without myelopathy. A spine specialist considers the complete clinical picture: symptoms, neurological examination findings, gait, reflexes, strength, dexterity, and MRI or other diagnostic imaging. This distinction matters because treatment is guided by evidence of spinal cord involvement, not neck imaging alone.
Symptoms That Should Not Be Dismissed
Cervical myelopathy may not feel dramatic at first. Some patients describe being less steady on stairs, dropping objects more often, or feeling that their legs are heavy or rigid. Others notice numbness in both hands, shock-like sensations into the arms or legs with neck movement, or difficulty completing tasks that require finger coordination.
As cord compression advances, symptoms can include weakness in the arms or legs, increasing falls, loss of walking endurance, and changes in bladder or bowel control. Symptoms do not always follow a predictable pattern. Neck pain may be present, but some patients with meaningful spinal cord compression have little or no neck pain.
Seek emergency care for sudden or rapidly worsening weakness, inability to walk, new loss of bladder or bowel control, numbness in the groin area, or neurological symptoms after a fall or accident. These symptoms can signal significant spinal cord injury or another neurological emergency that should not wait for a routine appointment.
Why Early Evaluation Matters
The spinal cord has limited tolerance for ongoing pressure. When compression causes myelopathy, the goal is to identify whether the condition is stable, progressing, or placing the patient at substantial risk of further neurological decline. Waiting until weakness or walking difficulty becomes severe can reduce the likelihood of a full neurological recovery.
This does not mean every patient with cervical stenosis needs immediate surgery. Some patients have narrowing without spinal cord symptoms and may be monitored with periodic examinations and imaging. Others have mild symptoms that can be assessed carefully over time. However, progressive myelopathy, meaningful weakness, impaired balance, or MRI evidence of significant cord compression often warrant a prompt surgical consultation.
A thorough evaluation can also help distinguish cervical myelopathy from conditions with overlapping symptoms, including peripheral neuropathy, carpal tunnel syndrome, stroke, Parkinsonian disorders, vitamin deficiencies, and lumbar spinal stenosis. Treating the wrong source of symptoms delays care and can leave spinal cord compression unaddressed.
Treatment Is Focused on Protecting the Spinal Cord
When cervical myelopathy is caused by mechanical compression, surgery is often the treatment most likely to prevent additional spinal cord injury. The purpose of surgery is decompression: creating more room for the spinal cord by removing the structure or structures causing pressure.
The appropriate procedure depends on where the compression is located, how many levels are involved, spinal alignment, instability, prior surgery, bone quality, and each patient’s overall health. For some patients, an approach from the front of the neck may be recommended. For others, a posterior approach may offer better decompression. In selected cases, stabilization or fusion is necessary; in others, motion-preserving or less disruptive options may be appropriate.
The trade-off is straightforward but significant. Surgery carries risks, and the recovery process requires preparation and follow-up. At the same time, continued cord compression may allow neurological function to deteriorate. A fellowship-trained neurosurgical evaluation helps clarify the anatomy, the urgency, the realistic benefits of treatment, and the risks of both action and delay.
Can Surgery Reverse Paralysis or Severe Weakness?
Surgical decompression can improve strength, balance, hand function, and walking for many patients, particularly when treatment occurs before severe, longstanding spinal cord damage. It is also used to reduce the risk of further decline. But surgery cannot guarantee that every lost function will return.
Recovery varies. Nerves and spinal cord tissue may recover gradually over weeks or months, and improvement can continue during rehabilitation. Patients with mild symptoms, shorter symptom duration, and less severe cord injury often have a more favorable outlook than those with advanced deficits. Even when symptoms do not completely resolve, stabilizing function and preventing additional loss can be a meaningful outcome.
Rehabilitation, fall prevention, medication management, and coordinated follow-up may all play a role after treatment. The plan should reflect the patient’s neurological status, work demands, activity goals, home support, and other medical conditions.
When to Seek a Cervical Spine Specialist
A specialist assessment is appropriate when neck symptoms are accompanied by hand clumsiness, progressive numbness, weakness, balance trouble, frequent falls, or changes in walking. It is especially important for patients who have been told they have cervical stenosis but are now noticing changes in function.
Bring prior MRI scans, radiology reports, and a clear description of when symptoms began and how they have changed. If you have already received a recommendation for surgery, a second opinion can clarify whether the proposed approach addresses the specific site of compression and whether other options should be considered.
At Total Spine & Brain Institute, the focus is on clear diagnosis and precise treatment planning for complex spine conditions. A careful neurological evaluation can help determine whether symptoms are related to cervical myelopathy, whether spinal cord compression is progressing, and what next step best protects your mobility and independence.
If you are noticing worsening balance, loss of hand function, weakness, or new changes in bladder or bowel control, do not assume these are routine effects of aging. Timely evaluation gives you the best opportunity to protect spinal cord function and make an informed decision before symptoms become more difficult to reverse.
